The Six-Cent Drug Nobody Will Test: Memantine as an Alternative to Opioids for Chronic Pain
Memantine is a cheap generic dementia drug that might help with chronic pain. Nobody has tested it properly, and that’s mostly about money.
Uncompetitive NMDA receptor antagonist · Off patent · ≈ $0.06 per 10 mg tablet · Evidence: thin, mixed, underpowered
What this document is
An argument for a publicly funded trial of memantine, an uncompetitive open-channel NMDA receptor antagonist, in chronic pain states characterized by central sensitization (fibromyalgia, complex regional pain syndrome, migraine) and in opioid tolerance and opioid-induced hyperalgesia. It covers the mechanistic rationale, the pharmacology relative to ketamine, dextromethorphan and PCP, the clinical trial record including the null and negative results, and the commercial history that explains why the question was dropped.
The evidence does not support memantine as an established analgesic. The only meta-analysis pooled eleven small trials and found no significant effect,1 and the only industry Phase III, in painful diabetic neuropathy, missed its primary endpoint.2 The claim here is narrower: the mechanism is sound, the positive signals cluster in a mechanistically coherent subset of conditions, a definitive trial would be inexpensive, and at an acquisition cost of about $0.06 per 10 mg tablet3 no sponsor has a commercial reason to run one. Note also that memantine has been tested for pain at 10–20 mg/day orally, a small fraction of the dose at which ketamine is used as an analgesic (section 04).
The question came from patients. This started with a conversation in 2015: I asked users of mobility aids what would most improve their quality of life, and a number of them named pain, and specifically the trade-off between sedation on opioids and uncontrolled pain. This is not clinical guidance and not a protocol.
In 2015 I asked people who use mobility aids what would make their lives better. Some of them talked about pain, and about the bargain it forced on them every day: stoned past the point of finishing a sentence, or lucid and in agony.
That bargain is why I’m writing this. I wanted to know whether anything gets you out of it.
The candidate I keep coming back to is memantine, an Alzheimer’s drug. It plugs the NMDA receptor, which is the same ion channel that ketamine, dextromethorphan and PCP plug, except that it does it so gently that people take it every day for years and never get high. It is also prescribed at a far smaller dose than ketamine is when ketamine is used for pain: 20 mg a day by mouth, against 80 mg or more per infusion into a vein.4 It has been off patent for years, and a US pharmacy pays about six cents for a tablet.3
My guess is that memantine could stand in for opioids in the kinds of chronic pain that come from central sensitization (fibromyalgia, complex regional pain syndrome, migraine), and maybe in the pain that opioids themselves cause. Nobody knows yet whether that guess is right, and as far as I can tell the reason nobody knows is money, not science.
Memantine is not an established treatment for chronic pain. The only meta-analysis pooled eleven small trials and found no significant effect,1 and the only Phase III trial a company ever paid for failed.2 So this is not a story about a miracle drug that somebody buried. It is a story about a trial that would be cheap to run and that nobody can make money from running.
None of this is medical advice, and it is definitely not a protocol. It’s an argument with the references attached, written so that you can hand it to a doctor or a funder and ask whether it’s worth a look.
| Mechanism | Sound. NMDA receptors drive central sensitization, opioid tolerance and opioid-induced hyperalgesia |
| Best human evidence | One 63-patient fibromyalgia trial, number needed to treat 6.2 |
| Worst human evidence | A failed Phase III in diabetic neuropathy; null results in postherpetic neuralgia and chronic phantom limb pain |
| Price | ≈ $0.06 per tablet, so no company profits from testing it |
| What is missing | A large, long, publicly funded trial in the right patients |
01 · Opioids are the wrong tool for most chronic pain
For chronic non-cancer pain the comparator is weaker than usually assumed. SPACE randomized 240 veterans with chronic back pain or hip or knee osteoarthritis pain to opioid or non-opioid pharmacotherapy for twelve months.5 Pain-related function did not differ between arms. Pain intensity on the Brief Pain Inventory favored the non-opioid arm (3.5 against 4.0), and medication-related symptoms were about twice as frequent on opioids.
Long-term µ-opioid agonism also produces two adaptations that work against analgesia: tolerance, a rightward shift of the dose–response curve, and opioid-induced hyperalgesia, a lowered nociceptive threshold that shows up between doses. Both are NMDA receptor dependent.6 The Mao–Price–Mayer model puts µ-opioid and NMDA receptor mechanisms in the same dorsal horn nociceptive neurons, with protein kinase C as the proposed link, and makes two predictions: hyperalgesia should travel with tolerance, and an NMDA antagonist should block both.6
In mice this mostly holds up. Memantine at 5–10 mg/kg, given before each morphine dose, prevents the rightward shift of the morphine dose–response curve in the tail-flick test, and in animals that are already tolerant, co-administered memantine reverses the tolerance. Dextromethorphan did not do the latter.7 One result goes the other way: in rats, memantine at 20 mg/kg/day had no effect on methadone-induced hyperalgesia.8
All of this is rodent data, so the opioid-sparing claim is a hypothesis and not clinical evidence.
Opioids are very good at acute pain. For chronic pain, the best long trial we have says they do no better than a plan that starts with acetaminophen.
That trial is called SPACE. It took 240 veterans with chronic back pain, or hip or knee osteoarthritis, put half on opioids and half on non-opioid medication, and followed them for a year.5 How well people could function came out the same in both groups. Pain intensity was actually better without opioids (3.5 against 4.0 on the Brief Pain Inventory), and the opioid group had twice as many medication-related symptoms.
I bring this up because it changes what memantine has to beat. It isn’t up against a drug that works well for chronic pain, it’s up against one that did no better than the alternatives over a year and that people overdose on.
There is a mechanical reason opioids let people down here. Taken for months, they make the nervous system more sensitive to pain, not less. The dose that worked in March has stopped working by September (that’s tolerance), and the pain between doses ends up worse than the pain you started with (that’s opioid-induced hyperalgesia).
Both of those run through the NMDA receptor,6 which is the whole reason I think memantine deserves a test against opioids: it blocks the receptor that makes opioids stop working.
02 · Chronic pain is a glutamate problem
Central sensitization is activity-dependent synaptic plasticity in nociceptive pathways, and it is NMDA receptor dependent. The receptor is a coincidence detector: at resting membrane potential the pore is occluded by Mg²⁺, and it conducts only when glutamate is bound and the postsynaptic membrane is already depolarized. Opening admits Ca²⁺ and potentiates the synapse,9 the same mechanism that underlies memory formation.
In the dorsal horn, sustained nociceptor input holds second-order neurons depolarized for long enough to relieve the Mg²⁺ block. Ca²⁺ entry strengthens the synapse, and the input–output gain of the circuit stays raised after the peripheral injury has resolved.
NMDA receptors come in at least two functional populations. Synaptic receptors drive plasticity and survival signaling. Extrasynaptic receptors, activated by glutamate spillover during excessive activity, oppose them, triggering CREB shut-off and cell-death pathways.9 This distinction matters in section 03.
The electrophysiological correlate is wind-up: repeated low-frequency C-fiber stimulation produces progressively larger dorsal horn responses, and NMDA antagonists abolish it. I am going from memory on that and have not attached a reference.
A µ-agonist reduces the afferent drive into this circuit without lowering its gain, and with chronic exposure it raises the gain (section 01). An NMDA antagonist acts on the gain itself. The glutamate side of this, raised free glutamate and failure of habituation, is in Biome of Overstimulation: Sensory Sensitivity as a Unifying Mechanism.
Chronic pain has a habit of carrying on after the injury has healed. What has happened is that the spinal cord and brain have turned up their own response to pain signals, and that turning-up depends on the NMDA receptor.
The NMDA receptor is a coincidence detector. While a neuron is at rest, the channel has a magnesium ion sitting in it like a cork. It only opens when glutamate is bound and the neuron is already depolarized, in other words when a signal lands on top of other signals. Then calcium floods in and the synapse gets stronger.9 This is how you form memories.
Your spinal cord does the same thing with pain. If pain fibers keep firing for long enough, the neurons in the dorsal horn stay depolarized long enough to pop the magnesium out. Calcium comes in, the synapse strengthens, and from then on the same input produces a bigger output. That is central sensitization: the gain on the pain system has been turned up, and it stays up after the original injury is gone.
I wrote about the neighbours of this idea in Biome of Overstimulation: Sensory Sensitivity as a Unifying Mechanism: excess free glutamate, sensory signals that never habituate, and the conditions that travel with them. Chronic pain is one of those conditions, and the hangover comparison from that post works here too.
An opioid turns down the signal coming into this system. It does nothing to the gain, and over months it actually turns the gain up. An NMDA antagonist goes for the gain.
03 · What memantine actually does
Memantine is an uncompetitive, voltage-dependent open-channel blocker that binds within the pore where Mg²⁺ binds. Three properties distinguish it from most blockers of this channel.
- Use dependence. Block requires an agonist-bound, open channel, so the fraction of receptors blocked rises with pathological activation.9
- Fast off-rate. It dissociates quickly enough that it does not accumulate in channels during brief, phasic synaptic transmission.9
- Extrasynaptic preference. At therapeutic concentrations it blocks extrasynaptic NMDA currents about twice as potently as synaptic ones.10
The net effect is suppression of tonic, excessive NMDA receptor activity with relative sparing of phasic transmission. A sensitized dorsal horn is tonic, excessive NMDA receptor activity, and that is the pharmacological case for testing it in chronic pain.
Pharmacokinetics: 20 mg/day gives steady-state plasma concentrations of 70–150 ng/mL (0.5–1 µM), with wide variation between individuals. The half-life is 60–80 hours, and most of the dose is excreted unchanged in urine.11 Two consequences follow. Steady state takes weeks, so a trial shorter than a month or two is testing the titration rather than the drug. And renal elimination falls by a factor of 7 to 9 in alkaline urine,11 so a patient who changes diet drastically, or starts living on antacids, can drift into a much higher exposure at an unchanged dose, and an adverse effect caused this way could be misattributed to the drug itself.
History: Eli Lilly synthesized it in 1963 as a candidate hypoglycemic agent, and it was inactive. Merz developed it, found some activity in Parkinson’s disease, and launched it for dementia in Germany in 1989, the year its NMDA mechanism was identified.12 EU approval for Alzheimer’s disease came in 2002 and FDA approval in 2003. Both repurposings came before the mechanism was known.
Memantine sits inside the open NMDA channel, in the spot where the magnesium sits, and blocks it. Plenty of drugs do that. Three things make this one different.
- It only blocks channels that are open. No glutamate, no block. Pharmacologists call this uncompetitive antagonism: the more pathologically active the receptor, the more of it gets blocked.9
- It leaves quickly. Its off-rate is fast enough that it doesn’t pile up in channels during brief, ordinary synaptic signaling.9
- It mostly blocks extrasynaptic receptors. At therapeutic concentrations it blocks extrasynaptic NMDA currents about twice as potently as synaptic ones.10
Put together, memantine damps down NMDA activity that is sustained and excessive, and mostly leaves ordinary signaling alone. A sensitized dorsal horn is sustained, excessive NMDA activity, which is the whole pharmacological case for trying it in chronic pain.
It also has a strange biography. Eli Lilly made it in 1963 hoping for a diabetes drug, and it didn’t lower blood sugar. Merz, in Germany, picked it up, noticed it did something in Parkinson’s disease, and ended up launching it for dementia in 1989, which happens to be the year somebody finally worked out that it acts on the NMDA receptor.12 The EU approved it for Alzheimer’s in 2002 and the US in 2003.
So this drug has already been repurposed twice, and both times before anyone knew how it worked.
04 · Comparison with the dissociatives
PCP, ketamine and dextromethorphan are open-channel NMDA receptor blockers acting in the same pore, and each has been tried as an analgesic. The table compares route of administration, psychotomimetic liability at clinical doses, the chronic pain evidence, and the commercial outcome.
PCP, ketamine and dextromethorphan all block the same channel as memantine, and every one of them has been tried for pain. Here they are side by side.
| Drug | Known as | How it is given | Dissociation at clinical dose | Chronic pain evidence | What the market did with it |
|---|---|---|---|---|---|
| PCP | The oldest of the group | Not given | Yes, and psychosis | None usable | Abandoned as an anesthetic; a street drug |
| Ketamine | Anesthetic, club drug, antidepressant | IV infusion, supervised; 80 mg or more per infusion4 | Yes | Moderate for CRPS, up to 12 weeks; no sustained benefit shown elsewhere4 | S-enantiomer sold as a nasal spray at $590–885 per session at launch13 |
| Dextromethorphan | Cough syrup | Oral, several times a day | Sedation, dizziness at pain doses | Diabetic neuropathy at a median 400 mg/day; nothing in postherpetic neuralgia14 | Combined with quinidine and sold at about $1,235 a month15 |
| Memantine | Alzheimer’s drug | Oral, once daily; 20 mg a day | No at 20 mg; yes at about eight times that16 | Section 05 | Generic, about $0.06 a tablet, no sponsor3 |
Memantine and ketamine are more alike than usually stated
The usual description of memantine as a low-affinity blocker and ketamine as a high-affinity one is not supported: IC50, blocking kinetics and voltage dependence at the NMDA receptor differ by less than a factor of two.17 The clinical divergence needs another explanation. There are three candidates, and they are not mutually exclusive.
- Receptor population and state. Memantine preferentially blocks extrasynaptic receptors,10 and it stabilizes a Ca²⁺-dependent desensitized state of the channel, which ketamine does not.18 This biases it toward receptors under prolonged activation.
- Block at rest. In physiological Mg²⁺, ketamine blocks NMDA receptors at resting membrane potential and memantine does not. Ketamine’s block of resting receptors dephosphorylates eEF2 and releases a burst of BDNF synthesis; memantine does neither.19 This is the best current account of why ketamine is a rapid-acting antidepressant and memantine is not.
- Exposure profile. Memantine is held at a steady-state concentration of 0.5–1 µM for weeks.11 Ketamine is infused to a peak and cleared within hours. The target is the same and the concentration–time profile is very different. This is my inference from the pharmacokinetics, and I have no citation for it.
You will often read that memantine is a “low-affinity” blocker and ketamine a “high-affinity” one. That turns out to be mostly wrong: their IC50, kinetics and voltage dependence at the NMDA receptor differ by less than a factor of two.17 And yet one of them is a dementia drug and the other is an anesthetic.
There are a few candidate explanations, and more than one could be true at once.
- Which receptors. Memantine favors extrasynaptic receptors,10 and it stabilizes a calcium-dependent desensitized state of the channel, which ketamine does not.18 It preferentially silences receptors that have been open too long.
- Magnesium. With physiological magnesium present, ketamine still blocks NMDA receptors at rest. Memantine does not. Ketamine’s block of resting receptors dephosphorylates eEF2 and releases a burst of BDNF synthesis; memantine does neither.19 This is the best current explanation for why ketamine is a rapid antidepressant and memantine is not.
- Exposure. Memantine is dosed to sit at 0.5–1 µM for weeks.11 Ketamine is infused to a peak and is gone in hours. The receptor is the same but the exposure over time is very different. This is my own reasoning from the pharmacokinetics. I don’t have a citation for it.
Memantine is a dissociative at high doses
The separation from the dissociatives is a matter of dose, not of kind. A French analysis of online self-reports found recreational doses averaging 156 mg, about eight times the maximum daily dose, producing a slow-onset dissociation that lasted a mean of 47 hours.16
The 60–80 hour half-life11 gives slow onset and a very long offset, which probably accounts for how rare recreational use is. The controlled-release coating of OxyContin could be defeated by crushing the tablet. Memantine’s slow kinetics are a property of the molecule, so there is no formulation to tamper with.
Take enough memantine and it behaves like the rest of the family. A French analysis of online self-reports found recreational users taking 156 mg on average, about eight times the maximum daily dose, and describing a dissociation that crept in over hours and then lasted, on average, 47 hours.16
A high that takes all afternoon to arrive and then stays for two days is not what most people are shopping for, which is probably why hardly anyone uses memantine recreationally. Compare OxyContin, which was sold with a slow-release coating you could defeat by crushing the tablet. Memantine is slow because of its half-life, so there is nothing to crush.
What the comparison says about pain
Ketamine has the strongest analgesic evidence of the group: moderate evidence in CRPS for up to 12 weeks, requiring supervised intravenous infusion, with no sustained benefit shown in other conditions.4
There is one head-to-head comparison. In the crossover trial of Sang and colleagues in painful diabetic neuropathy, pain fell 33% on dextromethorphan (median dose 400 mg/day, several times the antitussive dose), 17% on memantine and 16% on the lorazepam active placebo. None of the differences was significant in the main trial, but dextromethorphan showed a dose-response in its responders, and memantine was indistinguishable from the active placebo.14
Dose is the main confound in this comparison. For analgesia the consensus guidelines recommend a first outpatient ketamine infusion of at least 80 mg over more than 2 hours, find moderate evidence that higher dosages over longer periods and more frequent administration work better, cite 0.35 mg/kg per hour over 4 hours daily for 10 days in CRPS, and describe multiday infusions of up to 7 mg/kg per hour under intensive care monitoring.4 Memantine is prescribed at 20 mg/day orally, and its positive pain trials used 10–20 mg/day. With potency at the receptor within a factor of two,17 memantine has been tested as an analgesic at a small fraction of the ketamine dose, and at a low steady concentration instead of a high peak.
So the apparent ranking is a ranking of regimens, not of molecules. Dose is not the whole story: trials have gone as high as a median 55 mg/day, and at about 156 mg memantine is itself a dissociative.16 But no trial has compared the two drugs at matched receptor occupancy.
On the short-trial data memantine is the weakest analgesic of the three, at a much smaller dose. It is also the only one whose tolerability and once-daily oral dosing would allow continuous use over years.
One caution about my own argument. If the magnesium result generalizes, memantine barely touches NMDA receptors at rest.19 That is the property that makes it tolerable. It may also be the property that limits it as an analgesic: a blocker that only engages during sustained depolarization should do most in a circuit that is being driven hard right now, and least in one whose sensitization has already been consolidated structurally.
That predicts memantine should do better at prevention than at reversal, and better in ongoing central sensitization than in old peripheral nerve injury. Section 05 looks roughly like that. No trial has been designed to test it, so it stays a hypothesis.
Of the four, ketamine has the best evidence for pain. But it means infusions and monitoring, and outside CRPS nobody has shown that the benefit lasts.4
Dextromethorphan and memantine have been compared head to head exactly once, in diabetic neuropathy. Pain fell 33% on dextromethorphan, 17% on memantine and 16% on the lorazepam control. None of those differences was significant in the main trial, but dextromethorphan, at a median 400 mg a day (several times what the cough-syrup label allows), showed a dose-response in the people who responded. Memantine could not be told apart from the control.14
The doses are nowhere near each other, and this matters more than anything else in this comparison. As a painkiller, ketamine is given at a minimum of 80 mg per infusion, straight into a vein over two hours or more, and the guidelines say that higher doses given for longer work better.4 For CRPS that means infusions every day for ten days. Memantine is prescribed at 20 mg a day, by mouth.
The two drugs block the channel about equally well.17 So memantine has been tried for pain at a small fraction of the dose at which ketamine works. When someone says memantine is a weaker painkiller than ketamine, they are comparing a small dose of one with a large dose of the other.
In the short trials we have, memantine is the weakest painkiller of the three, at a much smaller dose. Its advantage is that it’s the only one you could realistically take every day for years.
05 · The evidence
The clinical evidence is about a dozen small, heterogeneous trials. The table lists the main ones by condition, including the null and negative results.
What we have clinically is a dozen or so small trials that don’t agree with each other. The table has the main ones, negative results included.
| Condition | What was done | Result |
|---|---|---|
| Fibromyalgia | RCT, 63 patients, 20 mg/day, 6 months20 | Positive. Pain VAS effect size d = 1.43 at 6 months; NNT 6.2 (95% CI 3 to 47) |
| CRPS | Small RCT, memantine + morphine against morphine + placebo, 8 weeks21 | Positive. Pain fell at rest and on movement with the combination, not with morphine alone |
| Phantom limb, recent amputation | One prospective study, case series22 | Positive |
| Phantom limb, over a year old | Four prospective studies22 | Negative |
| Postherpetic neuralgia | Pooled RCTs23 | Null. Effect size 0.03 |
| Diabetic neuropathy | Crossover RCT against active placebo14; industry Phase III2 | Negative. 17% pain reduction against 16% on control; Phase III missed its endpoint |
| Pain after surgery (prevention) | Two trials1 | Positive. −1.02 units on the pain scale |
| Episodic migraine | Two RCTs, 109 patients, 10 mg/day24 | Positive. −1.58 migraine days a month |
| All chronic pain, pooled | Meta-analysis, 11 trials1 | Not significant. −0.58 units (95% CI −1.31 to 0.14), I² = 82%, low quality |
The pattern
The results sort by pain mechanism and by chronicity. Memantine is null or negative in established peripheral neuropathic pain: postherpetic neuralgia, phantom limb pain of more than a year’s standing, painful diabetic neuropathy. It is positive, in small trials, where the process is central and either recent or ongoing: fibromyalgia, CRPS, acute post-amputation pain, perioperative prevention, and migraine prophylaxis.
The fibromyalgia trial was designed on magnetic resonance spectroscopy findings of raised glutamate in the insula, hippocampus and posterior cingulate of fibromyalgia patients.25 A 2024 network meta-analysis of 38 migraine trials ranked memantine among the more effective preventives, with the lowest dropout rate of any drug compared, though the interval on the dropout estimate includes no difference.26
This is a post hoc reading of a small evidence base. No trial has been designed to test it.
When I look at that table I see a pattern. Memantine fails in peripheral neuropathic pain that has been there a long time: old shingles, old amputations, diabetic nerves. It works, in small trials, where the problem is central and either recent or still going on: fibromyalgia, CRPS, fresh amputations, surgery that hasn’t happened yet, migraine.
The fibromyalgia trial was built on spectroscopy showing raised glutamate in the insula, hippocampus and posterior cingulate of people with fibromyalgia.25 And a 2024 network meta-analysis of 38 migraine trials put memantine among the more effective preventives, with the lowest dropout rate of any drug compared, although the interval on that last estimate includes no difference.26
To be clear, this is me reading a table, not a finding. Nobody has designed a trial to test it.
Checking the pattern with numbers
A subgroup meta-analysis by pain mechanism. The seven comparisons with extractable data (190 patients) were grouped following the 2025 Cochrane review of NMDA antagonists, which sorts these trials into peripheral neuropathic pain, CRPS and fibromyalgia;27 CRPS and fibromyalgia are combined here as the central sensitization group.
Pooled, the central group gives g = −1.36 (95% CI −1.83 to −0.89; 2 comparisons, 83 patients)2028 and the peripheral group g = −0.04 (−0.16 to +0.08; 5 comparisons, 107 patients). All seven together give −0.35 (−0.83 to +0.14) with I² = 81%, in line with the published meta-analysis.1 The between-group difference is −1.32 (95% CI −1.96 to −0.69, p = 0.003), and within each group I² is 0%.
Methods: the effect size is Hedges’ g on end-of-treatment pain. The model is random-effects with REML, and the group difference is a meta-regression with a Knapp–Hartung test on 5 degrees of freedom. For the crossover trial I used the paired difference and its confidence interval, standardized by the between-patient SD.14
The result holds up when I change the choices. Using change from baseline for the CRPS trial, which had a baseline imbalance of 1.3 points, the difference is −1.19 (p = 0.005). Treating the crossover periods as independent groups, it is −1.36 (p = 0.005).
Two effect sizes come from an earlier meta-analysis and not from the papers themselves.23 One prevention trial is plotted but not pooled.29 The chronic phantom limb trial is the one that leans toward placebo.30
One oddity in the source data. The crossover paper prints every ± as a standard error. For its postherpetic arm that can’t be right, because it would mean a standard deviation of 28 on a 20-point scale. I treated those values as standard deviations.
So I tried to test it myself, as far as the published numbers allow. I pooled the trials that had usable numbers and split them by pain type. The split follows the 2025 Cochrane review of NMDA antagonists, which sorts these trials into peripheral neuropathic pain, CRPS and fibromyalgia;27 I put CRPS and fibromyalgia together as the central group.
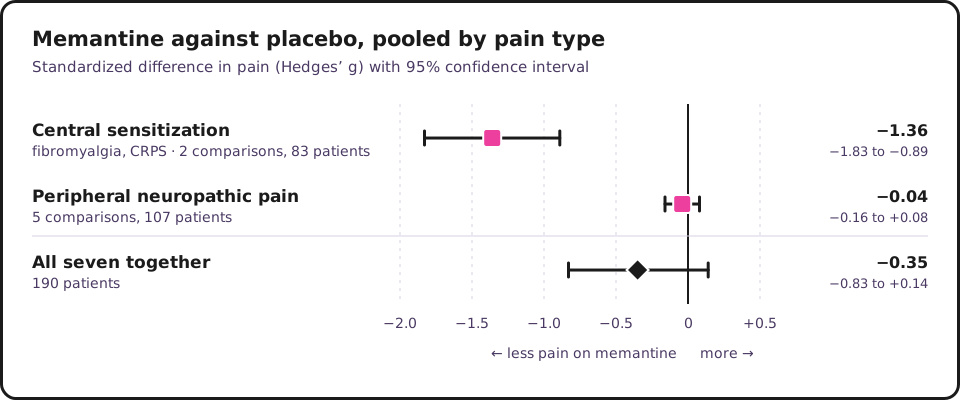
| Group | Comparisons | Patients | Effect size (95% CI) |
|---|---|---|---|
| Central sensitization (fibromyalgia, CRPS) | 2 | 83 | −1.36 (−1.83 to −0.89) |
| Peripheral neuropathic pain | 5 | 107 | −0.04 (−0.16 to +0.08) |
| All seven together | 7 | 190 | −0.35 (−0.83 to +0.14) |
Negative means less pain on memantine. The difference between the two groups is −1.32 (95% CI −1.96 to −0.69, p = 0.003).
Lump all seven comparisons together and you get nothing significant, plus a lot of disagreement between trials (I² = 81%), which is exactly what the published meta-analysis found.1 Split them by pain type and the disagreement disappears: I² is 0% in each group.
⚠ How much this is worth
Not much yet. The split came from looking at these same trials, so this is not an independent test.
The central group is two trials and 83 patients.2028 Without the fibromyalgia trial the difference is no longer significant (p = 0.07). With the stricter interval recommended for this few trials, the central estimate runs from −4.41 to +1.69.
Six trials had no numbers I could use. Three small ones reported no effect. The largest, 421 people with diabetic neuropathy, reported a benefit at 40 mg, and that goes against the pattern.31 The phase III that followed it failed.2
The two central trials also differ from the others in ways that have nothing to do with pain type. The fibromyalgia trial ran six months, and no peripheral trial in this analysis ran longer than nine weeks. The peripheral comparisons that carry the most weight used an active placebo, and the central trials did not. In the CRPS trial, everyone was also on morphine.
The number
The number needed to treat in the fibromyalgia trial was 6.2 (95% CI 3 to 47).20 For reference, the pooled NNTs in neuropathic pain are 3.6 for tricyclic antidepressants, 6.4 for SNRIs, 7.7 for pregabalin and 4.3 for strong opioids.32 The point estimate sits with the SNRIs. The comparison is indirect and across different conditions, and the upper bound of the interval is compatible with no clinically useful effect.
In fibromyalgia the number needed to treat was 6.2.20 For comparison, the pooled NNTs for the drugs we actually prescribe for neuropathic pain are 3.6 for tricyclics, 6.4 for SNRIs, 7.7 for pregabalin and 4.3 for strong opioids.32 Taken at face value, memantine in fibromyalgia is about as good as the SNRIs and better than pregabalin.
⚠ An honest caveat
That confidence interval runs from 3 to 47. It comes from one trial of 63 people in one Spanish city, and the comparison above is across different conditions. A number needed to treat of 47 is a drug that doesn’t work.
The pooled analysis is not significant.1 The only large, well-funded trial ever run failed.2 If a company were selling a patented drug on this evidence, I’d be writing a post about how they were overselling it.
I’m not saying memantine works. I’m saying we don’t know, it would be cheap to find out, and nobody has in more than twenty years.
On replacing opioids specifically
The opioid-sparing evidence is thinner still. It consists of the rodent tolerance data (section 01); one small randomized trial in CRPS in which memantine plus morphine reduced pain at rest and on movement and morphine plus placebo did not;21 and one Medicare claims analysis suggesting an opioid-sparing association in older adults with dementia and chronic pain, whose authors cannot establish temporal order.33 That justifies a trial and does not justify prescribing.
On the pooled result: an I² of 82% says the eleven trials are not measuring one thing.1 Pooling fibromyalgia with postherpetic neuralgia and asking whether memantine “works for chronic pain” is like averaging the truth of a theorem over the cases where its hypotheses hold and the cases where they don’t. The useful question is which pain mechanisms it works for.
Dose is the second unknown. The trials above ran from 10 mg to a median 55 mg a day. The early industry trial that came out positive in diabetic neuropathy used 40 mg in about 420 patients;2 the Alzheimer’s dose, and the fibromyalgia dose, is 20. Nobody has run a dose-response study of memantine in pain.
Then there is blinding. An NMDA antagonist with noticeable CNS effects unblinds itself against an inert placebo. Sang and colleagues used lorazepam as an active placebo for exactly this reason,14 and it bothers me that against an active placebo memantine’s effect vanished. As far as I can tell from the abstracts, the positive trials used inert placebo. That helps the skeptic’s case more than mine.
The claim in my own title has even less under it. There’s the mouse data in section 01, and one randomized trial in which memantine made morphine work in CRPS when morphine alone didn’t.21 There is also a single Medicare claims study suggesting memantine may be opioid-sparing in older adults with dementia and chronic pain, whose own authors say they can’t tell which came first.33
That is everything I found. To me it’s enough to justify a trial, and nowhere near enough to justify a prescription.
06 · Why nobody ran the trial
Memantine did once have a commercial pain program. It ended in 2003, and what the company did afterwards is a tidy lesson in incentives.
Back in 2001, analysts expected Forest Laboratories to file memantine for neuropathic pain in 2003.34 Pain was where the money was: Neurobiological Technologies, the small company that had done the early work, stood to collect a 13% royalty on pain sales against 1% on Alzheimer’s.35 An earlier trial at 40 mg had even come out positive.2
Then, in May 2003, the confirmatory Phase III in diabetic neuropathy missed its primary endpoint.2 Forest said it would run another Phase II and maybe file by 2006.36 Five months later memantine was approved for Alzheimer’s, and no pain indication ever followed.
So: one failed trial, in one condition, in exactly the kind of pain where memantine looks worst, and that was more or less the end of industry interest. I don’t even think it was irrational. If you have a freshly approved blockbuster and a patent clock running, why would you pay for a second expensive attempt at figuring out which pain patients respond?
It made perfect business sense, and the question stayed unanswered.
What the company did before the patent expired
With generic memantine due in 2015, Forest (which Actavis bought in the middle of all this) announced in 2014 that it would pull the twice-daily tablet and leave only a newer once-daily capsule, Namenda XR. The idea was to move people with Alzheimer’s disease onto the new version before the cheap one existed, so that pharmacists would have nothing to substitute. The industry calls this a hard switch.
New York’s attorney general sued. In May 2015 the Second Circuit upheld an injunction, the first time an appeals court had ruled that a product hop can violate the Sherman Act.37 A class action by direct purchasers, which also alleged a pay-for-delay deal with a generic manufacturer, settled for $750 million on the day the trial was supposed to open. The company admitted nothing.38
So in the last years of memantine’s exclusivity, the pain program sat untouched while the company put its energy into moving dementia patients from two tablets to one capsule to keep the generics out.
I don’t think Forest was unusually wicked. Every step was what a profit-maximizing company would do. It’s just that none of those steps involved finding out whether the drug helps people in pain.
The problem of new uses
Once a drug goes generic, the incentive drops to zero. If one company pays for a trial in a new indication, every other manufacturer gets to sell the same tablets on the strength of it. Legal scholars call this the problem of new uses, and it applies to roughly 2,000 off-patent drugs.39 Health economists have been saying for years that generic repurposing needs public money, because no private party is going to supply it.40
Memantine’s price tells the same story. A US pharmacy buys a 10 mg tablet for 6.4 cents.3 The “average retail price” of 28 of them is $145, and a discount card gets that down to $4.68.41 So the same box costs $1.80, $4.68 or $145 depending on who’s paying and how, and not one of those numbers tells you what the drug is worth.
What happened to the related drugs
Now look at what happened to its cousins, ketamine and dextromethorphan.
Ketamine is generic. So its S-enantiomer was put in a nasal spray, wrapped in new patents, and launched as Spravato at $590 to $885 per session.13 ICER, the US cost-effectiveness body, priced a year of it at about $32,400, found too little evidence that it beat plain generic ketamine, and pointed out that it cost roughly ten times the intravenous generic.42
Dextromethorphan is cough syrup. Add a little quinidine to slow its metabolism and you get Nuedexta, at around $1,235 a month.15 In 2019 its maker agreed to pay more than $108 million over kickbacks to doctors and misleading marketing in nursing homes, for use on dementia patients it was never approved for.43
Both times, an old NMDA antagonist looked promising, and both times nobody tested the old generic drug. They built a version that could be patented.
In fairness, esketamine did get real trials out of this, and that is the best argument for patents there is: exclusivity pays for evidence. The flip side is that a drug with no exclusivity gets no evidence. Memantine is the example. Nobody owns it, so nobody paid for the trials, so a pain doctor wondering whether to try it has almost nothing to go on.
07 · CBD: the opposite case
Cannabidiol is the mirror case: a non-opioid with a large consumer market for pain and almost no supporting trial evidence. If incentives determine what is tested and sold (section 06), there should be compounds that sell without evidence as well as compounds with a rationale that go untested. The table sets the two side by side.
Cannabidiol (CBD) is memantine’s mirror image: a non-opioid that is sold for pain, with an enormous market and almost no evidence behind it.
If incentives decide what gets tested and sold, which is what I argued in section 06, then there ought to be drugs that sell well without ever being tested. CBD is one. Anyone can sell it, nobody has to show that it works, and people in pain buy it.
| Memantine | CBD | |
|---|---|---|
| Proposed target | One: the open NMDA channel | Many: 5-HT1A, glycine receptors, TRP channels, GPR55, σ144 |
| Randomized pain trials | A dozen, mixed (section 05) | 16 with verified CBD; 15 found no benefit45 |
| What is in the box | A regulated tablet | Accurately labeled in 24% of 89 products tested46 |
| Known harm at usual dose | Dizziness, headache20 | Liver enzymes over three times normal in 5.6% of healthy adults at four weeks47 |
| Who sells it | Generic manufacturers, at six cents | Supplement companies, shops, online sellers |
| The patented version | None | Epidiolex: $32,500 a year at launch, $1.06 billion in 2025 sales4849 |
What it does
CBD is not an NMDA channel blocker and is not a dissociative. Its pharmacology is promiscuous: it facilitates 5-HT1A and glycine receptor function and impairs GPR55 and several TRP channels, at concentrations from nanomolar to micromolar.44 With that many targets a mechanism can be proposed for almost any indication, and any single one is hard to test.
One target converges on the NMDA receptor. In mice CBD behaves as a σ1 receptor antagonist: it weakens the association of σ1 with the NR1 subunit of the NMDA receptor, enhances morphine antinociception and reduces NMDA-induced seizures.44 CBD may therefore reduce NMDA receptor activity indirectly, by a route distinct from open-channel block. This is rodent data only.
CBD is not a dissociative and it doesn’t block the NMDA channel. What it does is hit a lot of targets at once: it facilitates 5-HT1A and glycine receptors and impairs GPR55 and several TRP channels, at concentrations anywhere from nanomolar to micromolar.44 With that many targets you can propose a mechanism for almost any condition, and you’ll have a hard time testing any single one.
One of those targets does lead back to the NMDA receptor. In mice, CBD behaves like a σ1 receptor antagonist: it weakens σ1’s binding to the NR1 subunit of the NMDA receptor, enhances morphine antinociception and reduces NMDA-induced seizures.44 So CBD may be turning down NMDA activity by a different route than memantine does. So far that has only been shown in mice.
What the trials say
A 2024 review identified sixteen randomized trials of pharmaceutical-grade CBD with a pain outcome, across twelve pain conditions, at doses from 6 to 1,600 mg and durations from a single dose to twelve weeks. Fifteen found no benefit over placebo.45 An updated systematic review of cannabinoids as opioid-sparing agents found the effect in preclinical and observational studies and not in the higher-quality randomized trials.50 CBD does have demonstrated efficacy in two severe childhood epilepsies, where proper trials were run.
I have to be consistent here. Those sixteen trials span twelve pain states, three routes of administration and a dose range of more than 250-fold.45 That is the same heterogeneity I used in section 05 to excuse memantine’s null pooled result, and I can’t have it both ways. Fifteen of sixteen negative is weaker as evidence of absence than it sounds.
A 2024 review rounded up every randomized trial that used pharmaceutical-grade CBD and measured pain. There were sixteen, across twelve pain conditions, with doses from 6 to 1,600 mg and durations from a single dose to twelve weeks. Fifteen found no benefit over placebo.45 The authors’ conclusion was that CBD for pain is expensive, ineffective and possibly harmful.
Replacing opioids goes the same way. An updated systematic review of cannabinoids in general found that the animal and observational studies suggest an opioid-sparing effect and the better randomized trials don’t.50
CBD does work for some things. It reduces seizures in two severe childhood epilepsies, and for those, proper trials were run.
What the market did
Product quality: in a 2022 analysis, 24% of 89 over-the-counter CBD topicals were accurately labeled, and THC was detected in 35% of 105 products, including some labeled THC-free.46 An earlier study of extracts sold online found 31% accurately labeled.51
Hepatic safety: in the FDA’s randomized trial in healthy adults, at 5 mg/kg/day for 28 days, 8 of 151 participants (5.6%) had liver enzyme elevations above three times the upper limit of normal, against none of 50 on placebo. Seven met withdrawal criteria for possible drug-induced liver injury, and all resolved within about two weeks of stopping.47 The study drug was Epidiolex itself, so the signal belongs to the molecule and not to a contaminant.
The tested product is Epidiolex: the same molecule, purified, trialed and patented. It launched at about $32,500 a year48 and earned $1,059 million in 2025, and its owner has settled with generic challengers for entry in the very late 2030s.49
Regulation: for seven years after the 2018 Farm Bill there was no federal product standard. In November 2025 Congress redefined hemp in a spending bill, with a cap of 0.4 mg total THC per container due to take effect on November 12, 2026. The law targets intoxicating hemp-derived THC and removes most full-spectrum CBD products with it; the industry estimates about 95% of hemp cannabinoid products, from a market it values at $28 billion.52
The untested version is sold to people in pain, and the tested version is sold to insurers.
Of 89 over-the-counter CBD topicals tested in 2022, only 24% contained what the label said, and THC turned up in 35% of 105 products, including some sold as THC-free.46 An earlier study of extracts sold online got 31%.51 And when the FDA ran its own trial of a consumer-range dose in healthy adults, 5.6% had liver enzymes above three times the upper limit of normal within four weeks, against nobody on placebo.47
The tested version is called Epidiolex. It’s the same molecule, purified, put through trials and patented, and it launched at about $32,500 a year.48 It earned $1,059 million in 2025, and its owner has settled with generic challengers for entry in the very late 2030s.49
The regulation went the way it went for opioids (section 08). For seven years after the 2018 Farm Bill there was no federal product standard at all. Then in November 2025 Congress redefined hemp inside a spending bill, with a cap of 0.4 mg total THC per container due to take effect on November 12, 2026. The law is aimed at intoxicating hemp THC, but it sweeps up most full-spectrum CBD products along the way. The industry says about 95% of hemp cannabinoid products will go, out of a market it values at $28 billion.52 First no standard, then a ban, and nothing resembling regulation in between.
Why this belongs in a post about memantine
The two cases are the same incentive failure seen from opposite directions. Memantine has a mechanism, a small number of positive trials, and no sponsor. CBD has a mass market for pain and fifteen negative trials out of sixteen. The populations overlap: patients whose opioids have been tapered or stopped and who were told there is nothing else. One of the review’s authors noted that chronic pain makes people vulnerable to promises of this kind.45
There is one difference I would defend. Memantine has one positive six-month trial in a population chosen on a mechanistic hypothesis.2025 CBD, for pain, has nothing equivalent. A properly designed CBD trial in a σ1-relevant pain state could still come out positive.
I don’t know whether σ1 antagonism and open-channel block would be additive. I haven’t found anyone who has tested it.
The two drugs are the same problem seen from opposite sides.
Memantine has a mechanism and a handful of positive trials, and nobody markets it for pain. CBD is marketed for pain everywhere you look, and fifteen of its sixteen trials were negative. Either way, companies sold what it paid to sell.
And the customers are often the same people. If your opioid prescription has been cut and you’ve been told there is nothing else, of course you’ll try the product that promises natural pain relief. One of the review’s authors made the point that chronic pain makes people vulnerable to promises like these.45
08 · Two policy failures
People with chronic pain in the US got screwed twice, in opposite directions, by the same institutions.
First, the overselling
Purdue Pharma has pleaded guilty to federal charges over OxyContin twice, once in 2007 and again in 2020.53 McKinsey earned $93 million advising Purdue over roughly fifteen years,54 which included a plan to “turbocharge” OxyContin sales while overdose deaths were climbing. In 2024 it paid $650 million to end the federal investigation, in a civil settlement that admits no liability.53
In November 2025 a bankruptcy judge approved a $7.4 billion plan under which the Sackler family pays about $6.5 billion over fifteen years.55 The individual victims share something over $850 million of that.56
Then, the crackdown
When prescribing finally was restricted, it was patients who paid for it, far more than the companies. Doctors under regulatory pressure cut doses or stopped prescribing altogether.
A study of 113,618 patients on stable long-term opioids found that tapering was followed by significantly more overdoses and mental health crises.57 That paper was corrected in 2022 for coding errors. The associations got smaller but held up, which is why I’m not quoting the original headline figure.
Prescriptions fell, and deaths kept rising for years anyway, because by then most of them were from illicit fentanyl. The CDC’s provisional count for 2025 is 69,973 overdose deaths, 44,564 of them involving opioids, down from 81,313 and 55,296 the year before.58 That makes three years of decline, and it is still about 120 opioid deaths a day.
So if you have chronic pain in America, you have been told three things in a row. First: this drug is safe, take more. Then: this drug is dangerous, you can’t have it. And finally: there’s nothing else.
That last one is false. There are other options, some of them with decent evidence, and then there’s memantine, which has never been properly tested.
Germany as a comparison
I’m writing this from Germany, where it went differently. Germany has ranked second in the world for opioid consumption per person and, by every account I can find, has no opioid epidemic.59 A systematic review of German prescribing found use going up and no sign of one.60
The usual explanation is the way the system is built. Opioids were never a first-line treatment here, prescribers face extra screening and paperwork, and addiction treatment is covered.61 One German primary-care paper lists what was different in the US: higher doses per patient, a heavy cost burden on individuals, lighter regulation, and a health system oriented toward profit.62
(Memantine itself, by the way, was on the market in Germany fourteen years before the FDA approved it.12)
I should admit that people use Germany to argue opposite things. The left reads it as proof that regulation and universal coverage work. Libertarians read it as proof that prescribing volume was never the cause, and that the real mistake was the American crackdown on prescribers. The German data fits both. The tapering study is evidence for the second reading, which is awkward for an argument like mine that blames the market, so you should know about both.
What both sides agree on is that the same drugs killed far fewer people in a different health system. So the crisis came out of how the drugs were sold and regulated, and not only out of the drugs.
09 · What a real trial would look like
A conventional parallel-group randomized trial would answer the question.
- Population. Fibromyalgia and CRPS first, where the signal is, with a second cohort of patients tapering long-term opioid therapy, where the need is. Enrich for mechanism and not for diagnosis: if the hypothesis is that memantine treats central sensitization, select and stratify on a measure of it, such as temporal summation on quantitative sensory testing. A trial that enrolls by diagnostic label will reproduce the heterogeneity that sank the meta-analysis.
- Dose. 20 mg and 40 mg/day against placebo. The only positive industry trial used 40.2 Both remain far below analgesic ketamine dosing (section 04), so a null result at 20 mg alone would not settle the question.
- Duration. At least six months. Steady state alone takes weeks,11 and the one positive long trial ran six months.20
- Design. Parallel groups, no crossover. With a half-life of 60–80 hours11 an adequate washout is weeks long, and carry-over biases a crossover toward the null. The head-to-head with dextromethorphan was a crossover.14 I have not checked its washout, and I would want to before leaning on it as hard as section 04 does.
- Control. An active placebo. An inert placebo is unblinded by a psychoactive drug.14
- Outcomes. Pain-related function and opioid dose in addition to pain intensity. SPACE used function as its primary outcome.5
- Prevention. Pre-register it separately. The perioperative signal1 and the acute-versus-chronic split in phantom limb pain22 both say timing matters, and that deserves its own trial, not a subgroup analysis.
- Sponsor. Public funding, since no company will pay.
The points on enrichment, crossover design and prevention are my own reasoning and are not taken from the literature.
On funding: the Purdue plan describes its payments as compensating victims and abating the opioid crisis, and it follows a $26 billion settlement with the distributors and Johnson & Johnson in 2022.55 A memantine trial would cost a tiny fraction of either. Under the bankruptcy plan Purdue’s assets pass to a new public benefit company, Knoa Pharma, chartered to make overdose-reversal and addiction-treatment drugs.55 A public benefit drug company is the kind of organization that could test a drug nobody can own. Whether it does is a political decision.
The trial that would settle this is a completely ordinary one, and the money to pay for it already exists.
- Who. Fibromyalgia and CRPS first, because that’s where the signal is. A second arm in people tapering long-term opioids, because that’s where the need is.
- Dose. 20 mg and 40 mg against placebo. The only positive industry trial used 40.2 Even 40 mg a day is far below the doses at which ketamine is given for pain (section 04).
- How long. Six months at least. Steady state alone takes weeks,11 and the one positive long trial ran six months.20
- Control. An active placebo. Sugar pills against a psychoactive drug are not blind.14
- Outcomes. Function and opioid dose, not only a pain score. SPACE used function as its main outcome.5
- Sponsor. Public money, since no company will pay.
About that money. The Purdue plan describes its payments as compensating victims and abating the opioid crisis, and it comes on top of a $26 billion settlement with the distributors and Johnson & Johnson in 2022.55 Finding out whether a six-cent non-opioid works seems to me like a fair use of abatement money, and a memantine trial would cost a tiny fraction of either settlement.
There is even a possible sponsor. Under the bankruptcy plan, Purdue’s assets pass to a new public benefit company, Knoa Pharma, chartered to make overdose-reversal and addiction-treatment drugs.55 A public benefit drug company is exactly the kind of organization that could test a drug nobody can own. Whether it will is a political decision.
10 · Taking this to your own doctor
Positioning first. Tricyclics, SNRIs and gabapentinoids carry a strong first-line recommendation in neuropathic pain, with NNTs of 3.6, 6.4 and 7.7; strong opioids sit third-line on a weak recommendation despite an NNT of 4.3, because of their harms.32 Ketamine infusion has better evidence in CRPS than memantine does.4 Dextromethorphan did better in the one head-to-head.14 CBD, on the trials so far, does not make the list.45 On current evidence memantine comes after all of these, and nobody has funded the trial that would show whether it belongs earlier.
What to establish before any off-label trial of therapy:
- Pain phenotype. Plausibly centrally sensitized (fibromyalgia, CRPS, migraine, widespread pain out of proportion to tissue damage), as opposed to established peripheral neuropathic pain.
- Prior treatment. Adequate trials of a tricyclic, an SNRI and a gabapentinoid.32
- Renal function. Memantine is eliminated renally and the dose is reduced in renal impairment.11
- Concomitant NMDA antagonists. Amantadine, dextromethorphan, ketamine.11
- Opioid therapy. In patients on long-term opioids, as an adjunct to a slow, supervised taper and not as a substitute for one. Tapering is itself associated with overdose and mental health crisis.57
- Off-label status. Who pays, and who monitors.
On self-sourcing: in the French analysis, people self-medicating at a mean of 23 mg/day for 15 weeks reported adverse effects in 77% of cases, including dissociation, clouded consciousness, anxiety and insomnia.16 Given the half-life, an error takes days to wear off; one accidental overdose took close to 100 hours to resolve.63
If you live with chronic pain, here are the questions I would take to a doctor.
- Is my pain plausibly centrally sensitized (fibromyalgia, CRPS, migraine, widespread pain out of proportion to any tissue damage) rather than an old peripheral nerve injury?
- Have the drugs with real evidence been tried and failed: a tricyclic, an SNRI, a gabapentinoid?32
- What is my kidney function? Memantine leaves through the kidneys and the dose comes down in renal impairment.11
- Am I taking anything else that acts on NMDA receptors, such as amantadine, dextromethorphan or ketamine?11
- If I am on long-term opioids, could this be tried alongside a slow, supervised taper rather than instead of one?
- This is off-label. Who pays, and who monitors?
⚠ Do not stop opioids abruptly
Tapering long-term opioids is itself associated with overdose and mental health crisis.57 Nothing in this document is a reason to stop or cut a prescribed opioid by yourself.
⚠ Do not source it yourself
Memantine circulates online as a self-experimentation drug. In the French analysis, people self-medicating at an average of 23 mg a day for 15 weeks reported adverse effects in 77% of cases: dissociation, clouded consciousness, anxiety, insomnia.16 The half-life means a mistake takes days to wear off. One accidental overdose took close to 100 hours to resolve.63
No doses are given here as a protocol
Deliberately. The numbers in this document are what trials used. Titration, kidney function and interactions are a prescriber’s job. This document exists to start a conversation, not to replace one.
I can’t tell you memantine works for pain, because it has never been properly tested. What I can tell you is that it costs six cents a tablet, that the last serious trial was twenty-three years ago, and that since then there has been an opioid epidemic and tens of billions of dollars in settlements. Somebody should run the trial.
Keyword summary
- central sensitization
- NMDA receptor, open-channel block
- opioid tolerance, opioid-induced hyperalgesia
- memantine, ketamine, dextromethorphan, PCP
- fibromyalgia, CRPS, migraine
- product hopping, hard switch
- the problem of new uses
- abatement
- cannabidiol (CBD), σ1 receptor
References
-
Kurian R, Raza K, Shanthanna H. A systematic review and meta-analysis of memantine for the prevention or treatment of chronic pain. European Journal of Pain. 2019;23(7):1234–1250. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Forest Laboratories discloses failure of pivotal memantine trial in diabetic neuropathic pain. BioWorld, May 2003. source ↗. Trade source; replace with the trial publication if one exists. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10
-
Memantine HCl 10 mg tablet, average pharmacy acquisition cost $0.06449 each, June 17, 2026, as listed by DrugPatentWatch. source ↗ ↩ ↩2 ↩3 ↩4
-
Cohen SP, et al. Consensus guidelines on the use of intravenous ketamine infusions for chronic pain. Regional Anesthesia and Pain Medicine. 2018;43(5):521–546. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Krebs EE, Gravely A, Nugent S, et al. Effect of opioid vs nonopioid medications on pain-related function in patients with chronic back pain or hip or knee osteoarthritis pain: the SPACE randomized clinical trial. JAMA. 2018;319(9):872–882. doi:10.1001/jama.2018.0899 source ↗ ↩ ↩2 ↩3 ↩4
-
Price DD, Mayer DJ, Mao J, Caruso FS. NMDA-receptor antagonists and opioid receptor interactions as related to analgesia and tolerance. Journal of Pain and Symptom Management. 2000;19(1 Suppl):S7–11. ↩ ↩2 ↩3
-
Popik P, Kozela E. Clinically available NMDA antagonist, memantine, attenuates tolerance to analgesic effects of morphine in a mouse tail flick test; and Popik P, Kozela E, Danysz W. Clinically available NMDA receptor antagonists memantine and dextromethorphan reverse existing tolerance to the antinociceptive effects of morphine in mice. Journals and years to be completed before print. ↩
-
Hay JL, Kaboutari J, White JM, Salem A, Irvine R. Model of methadone-induced hyperalgesia in rats and effect of memantine. European Journal of Pharmacology. 2010;626(2–3):229–233. source ↗ ↩
-
Lipton SA. Paradigm shift in neuroprotection by NMDA receptor blockade: memantine and beyond. Nature Reviews Drug Discovery. 2006;5:160–170. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Xia P, Chen HS, Zhang D, Lipton SA. Memantine preferentially blocks extrasynaptic over synaptic NMDA receptor currents in hippocampal autapses. Journal of Neuroscience. 2010. source ↗ ↩ ↩2 ↩3 ↩4
-
Ebixa (memantine hydrochloride) product monograph. Lundbeck Canada. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12
-
J&J foresees broad insurance coverage for Spravato nasal spray. Scrip, 2019. source ↗ ↩ ↩2
-
Sang CN, Booher S, Gilron I, Parada S, Max MB. Dextromethorphan and memantine in painful diabetic neuropathy and postherpetic neuralgia: efficacy and dose-response trials. Anesthesiology. 2002;96(5):1053–1061. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10
-
Nuedexta in agitated dementia. The Carlat Psychiatry Report. source ↗ ↩ ↩2
-
Memantine: dissociative disorders. Prescrire International. 2021;30(227):159. source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Johnson JW, Glasgow NG, Povysheva NV. Recent insights into the mode of action of memantine and ketamine. Current Opinion in Pharmacology. 2015;20:54–63. source ↗ ↩ ↩2 ↩3 ↩4
-
Glasgow NG, et al. Memantine and ketamine differentially alter NMDA receptor desensitization. Journal of Neuroscience. 2017;37(40):9686–9704. source ↗ ↩ ↩2
-
Gideons ES, Kavalali ET, Monteggia LM. Mechanisms underlying differential effectiveness of memantine and ketamine in rapid antidepressant responses. PNAS. 2014;111(23):8649–8654. source ↗ ↩ ↩2 ↩3
-
Olivan-Blázquez B, et al. Efficacy of memantine in the treatment of fibromyalgia: a double-blind, randomised, controlled trial with 6-month follow-up. Pain. 2014;155(12):2517–2525. doi:10.1016/j.pain.2014.09.004 source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Behandlungsinduzierte kortikale Reorganisation und Analgesie bei neuropathischen Schmerzen: eine fMRI- und MEG-Studie. Dissertation, Universität Tübingen. source ↗. Thesis record; replace with the journal publication before print. ↩ ↩2 ↩3
-
Loy BM, Britt RB, Brown JN. Memantine for the treatment of phantom limb pain: a systematic review. Journal of Pain & Palliative Care Pharmacotherapy. 2016. ↩ ↩2 ↩3
-
NMDA receptor antagonists for the treatment of neuropathic pain. Systematic review. source ↗. Author list and journal details to be completed before print. ↩ ↩2
-
Mondia MWL, et al. Memantine for episodic migraine: a systematic review and meta-analysis. Acta Medica Philippina. source ↗ ↩
-
Olivan-Blázquez B, et al. Evaluation of the efficacy of memantine in the treatment of fibromyalgia: study protocol. Trials. 2013;14:3. source ↗ ↩ ↩2 ↩3
-
Li G, Qu B, Zheng T, Duan S, Liu L, Liu Z. Role of memantine in adult migraine: a systematic review and network meta-analysis. Frontiers in Pharmacology. 2024;15:1496621. source ↗ ↩ ↩2
-
Ferraro MC, et al. Ketamine and other NMDA receptor antagonists for chronic pain. Cochrane Database of Systematic Reviews. 2025. CD015373. source ↗ ↩ ↩2
-
Gustin SM, et al. NMDA-receptor antagonist and morphine decrease CRPS-pain and cerebral pain representation. Pain. 2010;151(1):69–76. source ↗ ↩ ↩2
-
Morel V, et al. Memantine before mastectomy prevents post-surgery pain: a randomized, blinded clinical trial in surgical patients. PLoS One. 2016;11(4):e0152741. source ↗ ↩
-
Maier C, et al. Efficacy of the NMDA-receptor antagonist memantine in patients with chronic phantom limb pain: results of a randomized double-blinded, placebo-controlled trial. Pain. 2003;103:277–283. source ↗ ↩
-
Memantine in the treatment of diabetics with painful peripheral neuropathy: a placebo-controlled phase IIB trial. Pain Medicine. 2002;3(2):182. Conference abstract. source ↗. Author list to be completed before print. ↩
-
Finnerup NB, Attal N, Haroutounian S, et al. Pharmacotherapy for neuropathic pain in adults: a systematic review and meta-analysis. Lancet Neurology. 2015;14(2):162–173. source ↗ ↩ ↩2 ↩3 ↩4 ↩5
-
Medicare claims study of memantine, cholinesterase inhibitors and opioid prescribing in older adults with dementia and chronic pain. source ↗. Citation to be completed before print. ↩ ↩2
-
Memantine drug profile recording analyst expectations of a 2003 neuropathic pain filing. PMID 12090556. source ↗ ↩
-
Namenda neuropathic pain trial. The Pink Sheet, 2003. source ↗ ↩
-
Appellate court weighs in on pharmaceutical “product hopping”: People of the State of New York v. Actavis PLC (2d Cir. 2015). JD Supra. source ↗ ↩
-
Allergan shelling out $750M to settle lawsuit over its Namenda “hard switch” campaign. Fierce Pharma, 2019. source ↗ ↩
-
van der Pol KH, et al. Drug repurposing of generic drugs: challenges and the potential role for government. Applied Health Economics and Health Policy. 2023. source ↗ ↩
-
Memantine retail and discount prices. SingleCare, 2026. source ↗ ↩
-
J&J’s Spravato for depression “should be much cheaper.” pharmaphorum, 2019. source ↗ ↩
-
US Department of Justice. Pharmaceutical company targeting elderly victims admits to paying kickbacks, resolves related False Claims Act violations. 2019. source ↗ ↩
-
Rodríguez-Muñoz M, Onetti Y, Cortés-Montero E, Garzón J, Sánchez-Blázquez P. Cannabidiol enhances morphine antinociception, diminishes NMDA-mediated seizures and reduces stroke damage via the sigma 1 receptor. Molecular Brain. 2018;11(1):51. source ↗ ↩ ↩2 ↩3 ↩4 ↩5
-
Moore A, Straube S, Fisher E, Eccleston C. Cannabidiol (CBD) products for pain: ineffective, expensive, and with potential harms. The Journal of Pain. 2024;25(4):833–842. doi:10.1016/j.jpain.2023.10.009 source ↗ ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Spindle TR, et al. Cannabinoid content and label accuracy of hemp-derived topical products available online and at national retail stores. JAMA Network Open. 2022;5(7):e2223019. summary ↗ ↩ ↩2 ↩3
-
Florian J, et al. Cannabidiol and liver enzyme level elevations in healthy adults: a randomized clinical trial. JAMA Internal Medicine. 2025;185(9):1070–1078. doi:10.1001/jamainternmed.2025.2366 summary ↗ ↩ ↩2 ↩3
-
GW Pharma launches first cannabis-derived drug in US. BioPharma Dive, 2018. source ↗ ↩ ↩2 ↩3
-
Jazz Pharmaceuticals plc. Form 10-K for fiscal year 2025. source ↗ ↩ ↩2 ↩3
-
Opioid-sparing effect of cannabinoids for analgesia: an updated systematic review and meta-analysis of preclinical and clinical studies. Neuropsychopharmacology. 2022. doi:10.1038/s41386-022-01322-4 summary ↗. Author list to be completed before print. ↩ ↩2
-
Bonn-Miller MO, Loflin MJE, Thomas BF, Marcu JP, Hyke T, Vandrey R. Labeling accuracy of cannabidiol extracts sold online. JAMA. 2017. doi:10.1001/jama.2017.11909 ↩ ↩2
-
Navigating new hemp laws: a major shift for the cannabis industry. Womble Bond Dickinson, on P.L. 119-37. source ↗ ↩ ↩2
-
McKinsey & Company to pay $650 million for role in opioid crisis. NPR, December 13, 2024. source ↗ ↩ ↩2
-
McKinsey to pay $650 million in opioid settlement with Justice Department. Wire report in West Hawaii Today, December 2024. source ↗ ↩
-
Purdue bankruptcy plan: approval, Fierce Pharma, November 2025 ↗; plan filing, Fierce Pharma ↗; Knoa Pharma, Bloomberg Law ↗ ↩ ↩2 ↩3 ↩4 ↩5
-
Purdue Pharma gets court approval to give more than $7.4B to creditors. Hartford Business Journal. source ↗ ↩
-
Agnoli A, Xing G, Tancredi DJ, Magnan E, Jerant A, Fenton JJ. Association of dose tapering with overdose or mental health crisis among patients prescribed long-term opioids. JAMA. 2021;326(5):411–419. doi:10.1001/jama.2021.11013. Corrected 2022. summary ↗ ↩ ↩2 ↩3
-
CDC National Center for Health Statistics. U.S. overdose deaths decrease for third consecutive year in 2025. May 13, 2026. source ↗ ↩
-
What the US and Canada can learn from other countries to combat the opioid crisis. Brookings, 2020. source ↗ ↩
-
Rosner B, et al. Opioid prescription patterns in Germany and the global opioid epidemic: systematic review of available evidence. PLOS One. 2019. source ↗ ↩
-
Luthra S. How Germany averted an opioid crisis. KFF Health News, 2019. source ↗ ↩
-
Study of prescription opioid misuse risk in German general practice. BMC Family Practice. 2018. source ↗. Author list and title to be completed before print. ↩
-
Memantine overdose case report. BMC Geriatrics. 2024. source ↗. Author list to be completed before print. ↩ ↩2
Comments
Sign in with GitHub to leave one.